
What Are Uppers and Downers? Drugs, Effects, and Risks

Uppers and downers are informal names for two drug classes that push the central nervous system in opposite directions. Uppers speed the body up, and downers slow it down.
Stimulants such as cocaine and Adderall raise heart rate, alertness, and energy. Depressants such as alcohol, Xanax, and heroin slow breathing, lower blood pressure, and dull reaction speed.
The two labels describe effect, not legality. Both classes contain prescription medicines and illegal street drugs.
Right Choice Recovery treats both drug classes at its outpatient center in Dayton, New Jersey. The sections below define each class, name the drugs inside it, and explain the danger the two create in combination.
Key Takeaways
- Stimulants were involved in 59% of the roughly 309,300 overdose deaths recorded in the United States between January 2021 and June 2024, according to CDC data published in JAMA. Opioids were co-involved in 43.1% of those deaths.
- In 2021, 84.5% of cocaine-involved overdose deaths in the Northeast also involved an opioid, the highest share of any United States region, per the CDC National Center for Health Statistics. New Jersey sits inside that region.
- Uppers elevate dopamine and norepinephrine at the synapse. Downers potentiate gamma-aminobutyric acid at the GABA-A receptor chloride channel, which is why the two classes produce opposite effects.
- No FDA-approved medication treats stimulant use disorder. Contingency management carries close to 40 years of clinical evidence and remains the strongest single intervention for the condition.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Are Uppers and Downers?
Uppers and downers are slang terms for stimulants and central nervous system depressants. Uppers accelerate signaling between the brain and body, and downers suppress it. The classification tracks the direction of a drug’s effect on the central nervous system, not its legal status.
A stimulant increases central nervous system activity by raising synaptic dopamine and norepinephrine. These two neurotransmitters govern attention, motivation, and the fight-or-flight response.
A central nervous system depressant reduces neuronal firing rate by potentiating gamma-aminobutyric acid, the brain’s primary inhibitory neurotransmitter. Reduced firing produces sedation, muscle relaxation, and slowed breathing.
Upper drugs and downer drugs occupy opposite ends of a single spectrum of drug addiction. Clinicians assess both classes against the same diagnostic framework because both hijack the same reward circuitry.
Which Drugs Are Uppers?
Uppers divide into three groups: prescription stimulants, illicit stimulants, and legal stimulants.
Prescription stimulants treat attention-deficit/hyperactivity disorder and narcolepsy:
- Methylphenidate reaches patients as Ritalin and Concerta. The Drug Enforcement Administration classifies methylphenidate as a Schedule II controlled substance.
- Mixed amphetamine salts reach patients as Adderall. Adderall carries the same Schedule II designation as methylphenidate.
- Lisdexamfetamine reaches patients as Vyvanse. The liver converts lisdexamfetamine into dextroamphetamine after ingestion.
Illicit and legal stimulants circulate outside the prescription supply:
- Cocaine blocks dopamine reuptake at the nucleus accumbens, which concentrates dopamine in the synapse and produces euphoria lasting 60 to 90 minutes.
- Methamphetamine forces dopamine release and resists enzymatic breakdown, which extends its effect to 8 to 12 hours.
- MDMA floods serotonin alongside dopamine and norepinephrine, producing both stimulant arousal and altered emotional processing.
- Caffeine and nicotine act on the same reward circuitry at lower intensity, which is why both meet the pharmacological definition of a stimulant.
Which Drugs Are Downers?
Downers divide into three groups: opioids, sedative-hypnotics, and alcohol.
Prescription sedative-hypnotics treat anxiety and insomnia:
- Alprazolam reaches patients as Xanax. Alprazolam binds the GABA-A receptor and increases chloride ion flow into the neuron.
- Diazepam and clonazepam reach patients as Valium and Klonopin. Both benzodiazepines produce longer sedation than alprazolam.
- Zolpidem and eszopiclone reach patients as Ambien and Lunesta. Clinicians group these non-benzodiazepine hypnotics as Z-drugs.
Opioids and other depressants dominate the illicit supply:
- Heroin, fentanyl, and oxycodone bind mu-opioid receptors and suppress the brainstem respiratory drive.
- Alcohol potentiates GABA and inhibits glutamate simultaneously, which makes it the most widely used depressant in New Jersey.
- GHB and barbiturates produce deep sedation at doses close to their toxic threshold.
- Xylazine, a veterinary sedative, now adulterates a growing share of the illicit fentanyl supply. Xylazine adulteration matters clinically because naloxone does not reverse it.
Cannabis resists clean classification. Cannabis produces sedation at some doses and tachycardia at others, so pharmacologists place it outside the stimulant-depressant binary rather than inside either class.
Why Do Uppers and Downers Lead to Addiction?
Uppers and downers lead to addiction because both classes overload the same dopaminergic reward pathway despite moving central nervous system activity in opposite directions. Repeated exposure downregulates dopamine receptor availability, which raises the dose required to reach the original effect.
Richard Solomon and John Corbit described this cycle in Psychological Review in 1974 as opponent-process theory. Every drug-induced pleasure state, which they called the A-process, triggers an opposing rebound state called the B-process.
The B-process strengthens with each repetition while the A-process weakens. This asymmetry explains the crash that follows a stimulant and explains why a person reaches for a downer to blunt it.
George Koob and Michel Le Moal extended the theory into a model of allostasis. Allostasis describes a reward baseline that never fully resets, which leaves the brain reward system shifted downward.
Neurobiological and Genetic Causes
Stimulants and depressants act on separate receptor systems. Stimulants elevate dopamine and norepinephrine in the ventral tegmental area and nucleus accumbens, while depressants potentiate gamma-aminobutyric acid at the GABA-A receptor chloride channel.
Chronic stimulant exposure reduces dopamine D2 receptor availability in the striatum. Reduced receptor density blunts response to ordinary rewards such as food, exercise, and social contact.
Genetics account for approximately 40% to 60% of the variance in substance use disorder risk, and a first-degree family history raises individual risk independent of environment.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking intensive outpatient care or simply need guidance on your mental health journey, we are here to help.
Developmental and Environmental Causes
Adverse childhood experiences drive substance use disorder risk in a dose-response pattern. Each additional adverse childhood experience raises the likelihood of later drug use, and four or more produce a multiple-fold increase.
Early age of first use compounds that risk. Adolescents who begin using before age 15 develop substance use disorders at substantially higher rates than adults who begin after 21, because the prefrontal cortex continues developing into the mid-twenties.
Co-Occurring Conditions and Substance-Related Pathways
Certain psychiatric conditions raise the likelihood of stimulant or depressant misuse through identifiable mechanisms.
Four co-occurring conditions appear most often alongside upper and downer use:
- Attention-deficit/hyperactivity disorder drives stimulant misuse because stimulants temporarily correct the executive dysfunction that defines the condition.
- Generalized anxiety disorder drives depressant misuse because benzodiazepines and alcohol suppress the physiological hyperarousal that anxiety produces.
- Post-traumatic stress disorder drives both patterns, since stimulants counteract emotional numbing while depressants suppress intrusive symptoms.
- Gambling disorder shares the dopaminergic vulnerability that stimulants exploit, which is why sports betting and stimulant use frequently appear in the same client.
Clinicians call this pattern the self-medication hypothesis, which holds that people select a drug class whose pharmacology matches the symptom they are suppressing.
How Long Do the Effects of Uppers and Downers Last?

Uppers and downers produce effects lasting from 60 minutes to 12 hours depending on the drug and route of administration. Onset ranges from under 1 minute for injected fentanyl to 60 minutes for oral amphetamine salts. Duration determines the window in which a second drug typically enters the body.
| Drug | Class | Onset | Peak | Duration |
|---|---|---|---|---|
| Cocaine (insufflated) | Upper | 1 to 3 minutes | 20 to 30 minutes | 60 to 90 minutes |
| Methamphetamine | Upper | 5 to 20 minutes | 1 to 3 hours | 8 to 12 hours |
| Mixed amphetamine salts | Upper | 30 to 60 minutes | 2 to 3 hours | 4 to 6 hours |
| MDMA | Upper | 30 to 60 minutes | 90 minutes to 3 hours | 4 to 6 hours |
| Alprazolam | Downer | 15 to 30 minutes | 1 to 2 hours | 4 to 6 hours |
| Heroin (injected) | Downer | 1 to 5 minutes | 10 to 30 minutes | 3 to 5 hours |
| Fentanyl (illicit) | Downer | Under 1 minute | 5 to 15 minutes | 1 to 2 hours |
| Alcohol | Downer | 10 to 30 minutes | 30 to 90 minutes | 2 to 4 hours |
The combined upper and downer cycle follows six measurable stages.
- 0 to 30 minutes. The stimulant takes effect. Heart rate, blood pressure, and body temperature rise together.
- 30 minutes to 2 hours. The stimulant peaks. Dopamine concentration reaches maximum and appetite and sleep drive disappear.
- 2 to 6 hours. The stimulant clears and the crash begins. Most people who combine drug classes introduce a depressant during this window.
- 6 to 12 hours. Depressant sedation overlaps residual stimulant load. The cardiovascular system carries opposing signals simultaneously.
- 12 to 48 hours. Rebound insomnia, dysphoria, and craving dominate. This stage produces the strongest pressure to redose.
- 48 hours to 10 days. Protracted withdrawal symptoms persist. Anhedonia and sleep disruption outlast the acute phase by several days.
Stage three carries the highest overdose risk, because the stimulant masking depressant sedation clears first and leaves the depressant load unopposed.
What Are the Side Effects of Uppers and Downers?
Uppers and downers produce opposite side effect profiles at every severity tier. Stimulants overdrive the cardiovascular and thermoregulatory systems, while depressants suppress respiration and consciousness. Severity escalates with dose, frequency, and the presence of a second substance.
Common Side Effects of Uppers and Downers
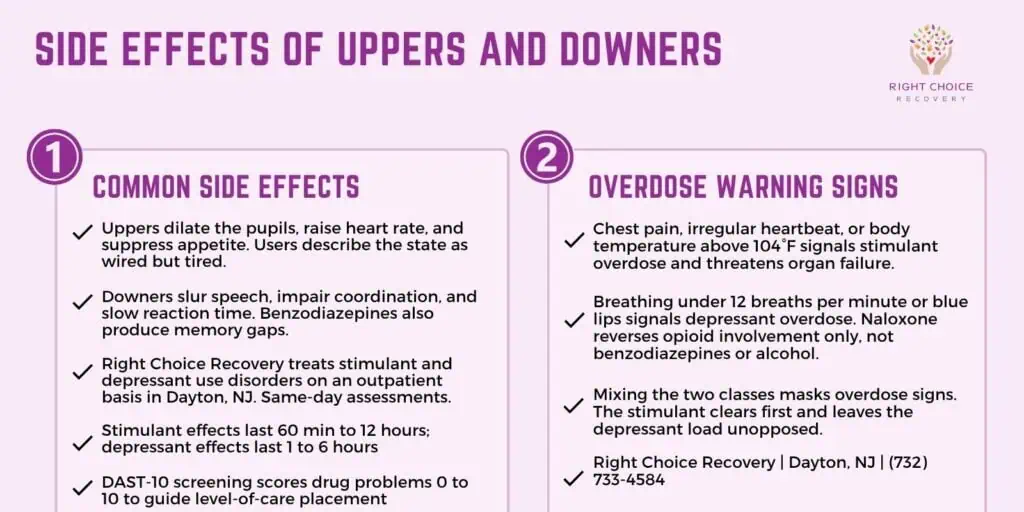
Routine side effects appear at typical recreational doses:
- Uppers dilate the pupils, raise heart rate, and suppress appetite. Users describe the state as wired but tired once the first dose begins clearing.
- Uppers disrupt sleep architecture and reduce total sleep time, which compounds fatigue across consecutive days of use.
- Downers slur speech, impair coordination, and slow reaction time. Users describe the state as taking the edge off.
- Downers produce anterograde memory gaps, which explains why benzodiazepine users lose blocks of time.
Rediscover Life at Right Choice Recovery
Get the compassionate health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our Facility
Severe Side Effects and Overdose Warning Signs
Emergency warning signs require immediate medical response:
- Chest pain or irregular heartbeat signals stimulant cardiotoxicity and precedes myocardial infarction.
- Body temperature above 104 degrees Fahrenheit signals stimulant hyperthermia and threatens organ failure.
- Seizure activity follows both stimulant overdose and abrupt depressant cessation.
- Breathing under 12 breaths per minute signals depressant-driven respiratory depression.
- Blue lips or fingertips signal cyanosis and confirm that oxygen delivery has already failed.
- Unresponsiveness to voice or touch indicates depressant overdose in progress.
Depressant overdose kills by suppressing the medulla oblongata, the brainstem structure that drives automatic breathing. Naloxone reverses this suppression when opioids cause it, but naloxone has no effect on benzodiazepine, alcohol, or xylazine involvement.
Long-Term Effects of Uppers and Downers
Sustained use produces distinct long-term damage in each class:
- Chronic stimulant use produces cardiomyopathy and accelerates coronary artery disease. Cocaine and methamphetamine both damage cardiac tissue directly.
- Chronic methamphetamine use damages dopaminergic nerve terminals. This damage produces cognitive deficits that persist for months into abstinence.
- Chronic stimulant use triggers persistent psychosis in a subset of users. Paranoia and hallucinations continue past the period of active intoxication.
- Chronic depressant use builds tolerance that drives dose escalation. Escalation narrows the gap between an effective dose and a fatal one.
- Abrupt benzodiazepine or alcohol cessation produces withdrawal seizures. This class of withdrawal kills, which is why medical supervision is mandatory.
How Are Stimulant and Depressant Use Disorders Diagnosed?
Clinicians diagnose against DSM-5-TR criteria rather than the informal upper and downer labels. The formal diagnoses are stimulant use disorder; opioid use disorder; and sedative, hypnotic, or anxiolytic use disorder. Neither slang term appears anywhere in DSM-5-TR.
The Drug Abuse Screening Test (DAST-10) is the standard screening instrument. The DAST-10 measures drug-related problem indicators across the previous 12 months and scores from 0 to 10.
DAST-10 scores map to five severity tiers. A score of 0 indicates no problems reported, and 1 to 2 indicates a low level. A score of 3 to 5 indicates a moderate level, 6 to 8 a substantial level, and 9 to 10 a severe level.
Two further scales grade withdrawal severity. The Clinical Institute Withdrawal Assessment for Alcohol, Revised (CIWA-Ar) grades alcohol withdrawal, and the Clinical Opiate Withdrawal Scale (COWS) grades opioid withdrawal. Both scores determine the level of care a patient requires.
What Is the Difference Between Uppers and Downers?
Uppers and downers separate on six observable physical markers. Pupil size, heart rate, speech pattern, body temperature, sleep, and appetite move in opposite directions between the two classes. These markers let a clinician or family member identify which class a person has taken.
| Marker | Uppers (stimulants) | Downers (depressants) |
|---|---|---|
| Pupil size | Dilated | Constricted with opioids, normal with benzodiazepines |
| Heart rate | Elevated above 100 beats per minute | Depressed below 60 beats per minute |
| Speech | Rapid and pressured | Slurred and slowed |
| Body temperature | Raised, with sweating and flushing | Lowered, with cool or clammy skin |
| Sleep | Suppressed for 8 to 24 hours | Induced within 30 minutes |
| Appetite | Suppressed | Variable, increased with cannabis and alcohol |
The uppers vs downers comparison reduces to one mechanism. Uppers increase the rate of signal transmission across the central nervous system, and downers decrease it.
That mechanical difference sets the danger profile. Stimulant overdose kills through cardiac and thermoregulatory failure, while depressant overdose kills through respiratory arrest. Alcohol use disorder follows the depressant pattern despite alcohol’s social acceptability.
What Happens When Someone Mixes Uppers and Downers?
Mixing uppers and downers does not cancel either drug out. The combination masks the warning signs of both while the physiological load on the heart and lungs compounds. The Centers for Disease Control and Prevention identifies this masking effect as a primary driver of unintentional overdose.
Combining drug classes is common rather than rare. Buxton and colleagues reported in BMJ Open in 2022 that among people who used both classes concurrently, 58.3% used downers followed by uppers, 24.8% used uppers followed by downers, and 59.9% mixed the two together.
Four mechanisms make the combination dangerous:
- Masking. The stimulant conceals depressant sedation, so the person continues dosing past the threshold at which sedation would normally stop them. According to CDC polysubstance use guidance, this modification of perceived effect makes overdose easier to reach.
- Cardiac oxygen mismatch. The stimulant raises myocardial oxygen demand while the depressant suppresses respiratory drive and reduces oxygen supply. The heart works harder on less oxygen.
- Offset asymmetry. The stimulant clears the body first and leaves the full depressant load unopposed. This sequence produces fatal respiratory depression hours after the last dose.
- Cocaethylene formation. Cocaine combined with alcohol produces cocaethylene in the liver, which carries greater cardiotoxicity than either drug alone.
Two combinations carry street names. A speedball combines cocaine or methamphetamine with heroin, and a goofball combines methamphetamine with fentanyl.
Fentanyl adulteration has made both combinations more lethal. A person who intends to use only a stimulant now risks opioid use disorder and fatal respiratory depression from a contaminated supply. The New Jersey Department of Health overdose dashboard tracks stimulant and opioid involvement together for this reason.
Are you covered for treatment?


Right Choice Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!How Is Addiction to Uppers and Downers Treated?
Treatment differs by drug class because withdrawal risk differs by drug class. Depressant withdrawal carries seizure risk and requires medical supervision, while stimulant withdrawal is psychologically severe but rarely life-threatening. Both classes respond to structured behavioral treatment at an outpatient level of care.
Contingency management holds the strongest evidence base of any intervention for stimulant use disorder, including every medication studied. The American Society of Addiction Medicine and the American Academy of Addiction Psychiatry named it a primary recommendation in their 2023 clinical practice guideline.
The pharmacological picture splits sharply between the two classes. No medication holds FDA approval for stimulant use disorder, while buprenorphine, methadone, and extended-release naltrexone all hold approval for opioid use disorder. Benzodiazepine dependence requires a structured taper rather than a blocking agent.
Four further approaches carry research support without FDA approval for stimulant use disorder:
- Bupropion, topiramate, and mirtazapine each reduce stimulant use in specific patient subgroups.
- Extended-release naltrexone combined with oral bupropion produced a 27% increase in methamphetamine-negative urine tests against 11% for placebo. Trivedi and colleagues reported the trial in the New England Journal of Medicine, and Li and colleagues extended it in Addiction.
- Transcranial magnetic stimulation reduces cocaine craving in early trials and holds FDA clearance for depression only.
- Psilocybin-assisted therapy and anti-cocaine immunotherapy remain in trials, as documented in NIDA overdose research.
How Does Right Choice Recovery Treat Uppers and Downers?

Right Choice Recovery treats stimulant and depressant use disorders at its outpatient center in Dayton, New Jersey. The facility runs chemical dependency and behavioral addiction tracks under one roof, which matters for stimulant clients whose use overlaps with sports betting or online gambling.
The Partial Care program runs Monday through Thursday from 9:00 AM to 2:00 PM and Friday from 9:00 AM to 12:00 PM. The intensive outpatient program adds an evening track meeting Monday through Thursday from 6:00 PM to 9:00 PM for clients who hold jobs.
“Clients who arrive using stimulants frequently disclose a second compulsion once the stimulant use stabilizes, and sports betting is the one we see most often. Treating the stimulant use alone leaves the reward pathway still under load.” Caitlin Moore, LPC, LCADC, CCS, ICGC-1, Clinical Director, Right Choice Recovery
The facility offers Vivitrol and Suboxone on site under medical supervision and holds in-network status with Tricare and VACCN. Adolescent programming serves ages 13 through 17.9, and a family program meets every Wednesday.
Frequently Asked Questions
Is alcohol an upper or a downer?
Alcohol is a downer. Alcohol potentiates gamma-aminobutyric acid and inhibits glutamate, which slows central nervous system activity. The initial disinhibition that makes alcohol feel stimulating reflects suppressed prefrontal control rather than genuine stimulation, and sedation follows as blood alcohol concentration rises.
Is marijuana an upper or a downer?
Marijuana is neither. Cannabis acts on the endocannabinoid system rather than on dopamine reuptake or GABA-A receptors, and it produces sedation at some doses and elevated heart rate at others. Pharmacologists classify cannabis separately from both stimulants and depressants for this reason.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What are the street names for uppers and downers?
Uppers circulate as speed, uppers, addys, crank, ice, blow, and snow. Downers circulate as downers, benzos, bars, tranks, and nods. Street vocabulary shifts by region and year, so recognizing a specific term matters less than recognizing the physical markers of each class.
Is caffeine considered an upper?
Caffeine is a stimulant by pharmacological definition. Caffeine blocks adenosine receptors, which increases alertness and raises heart rate. Caffeine differs from controlled stimulants in potency rather than mechanism, and it does not produce the dopamine surge that drives compulsive use of cocaine or methamphetamine.
Can teenagers develop an addiction to uppers or downers?
Teenagers develop substance use disorders at higher rates than adults who begin later. The prefrontal cortex continues developing into the mid-twenties, which leaves adolescent impulse control incomplete during exposure. Right Choice Recovery treats adolescents from age 13 through 17.9 in dedicated programming separate from adult groups.
Is it safe to quit uppers or downers cold turkey?
Quitting depressants cold turkey is dangerous. Abrupt cessation of benzodiazepines or alcohol produces withdrawal seizures that kill, so both require a medically supervised taper. Stimulant cessation produces severe depression, fatigue, and craving without the same physical danger, though clinical support improves outcomes substantially.
Does naloxone reverse a stimulant overdose?
Naloxone does not reverse a stimulant overdose. Naloxone displaces opioids from mu-opioid receptors and has no action on dopamine or norepinephrine. Emergency responders still administer naloxone when a stimulant overdose is suspected, because fentanyl contamination of the stimulant supply makes opioid involvement likely.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking intensive outpatient care or simply need guidance on your mental health journey, we are here to help.
Can a person have both a stimulant and a depressant use disorder?
DSM-5-TR permits concurrent diagnoses across substance classes. A person can meet full criteria for stimulant use disorder and opioid use disorder simultaneously, and each diagnosis is graded separately for severity. Concurrent diagnoses change the treatment plan, since each class requires a different withdrawal protocol.
References
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- American Society of Addiction Medicine & American Academy of Addiction Psychiatry. (2023). Clinical practice guideline on the management of stimulant use disorder.
- Buxton, J. A., Lock, K., Steinberg, A., Mehta, A., Papamihali, K., Lukac, C. D., Young, S., Graham, B., & Fleury, M. (2022). Motivations for concurrent use of uppers and downers among people who access harm reduction services in British Columbia, Canada. BMJ Open, 12(5), e060447.
- Centers for Disease Control and Prevention. (2024). Polysubstance use facts. National Center for Injury Prevention and Control.
- Li, M. J., Chau, B., Belin, T., Carmody, T., Jha, M. K., Marino, E. N., & Shoptaw, S. J. (2024). Extended observation of reduced methamphetamine use with combined naltrexone plus bupropion in the ADAPT-2 trial. Addiction.
- National Institute on Drug Abuse. (2025). Drug overdose deaths: Facts and figures. National Institutes of Health.
- New Jersey Department of Health. (2026). New Jersey overdose data dashboard. Office of Population Health.
- Solomon, R. L., & Corbit, J. D. (1974). An opponent-process theory of motivation: I. Temporal dynamics of affect. Psychological Review, 81(2), 119–145.
- Spencer, M. R., Miniño, A. M., & Garnett, M. F. (2023). Co-involvement of opioids in drug overdose deaths involving cocaine and psychostimulants, 2011–2021 (NCHS Data Brief No. 474). National Center for Health Statistics.
- Substance Abuse and Mental Health Services Administration. (2024). Contingency management advisory (PEP24-06-001).
- Trivedi, M. H., Walker, R., Ling, W., dela Cruz, A. M., Sharma, G., Carmody, T., Ghitza, U. E., Wahle, A., Kim, M., Shores-Wilson, K., Sparenborg, S., Coffin, P., Schmitz, J., Wiest, K., Bart, G., Sonne, S. C., Wakhlu, S., Rush, A. J., Nunes, E. V., & Shoptaw, S. (2021). Bupropion and naltrexone in methamphetamine use disorder. New England Journal of Medicine, 384(2), 140–153.
Medically reviewed by Caitlin Moore, LPC, LCADC, CCS, ICGC-1, Clinical Director at Right Choice Recovery. Last reviewed August 21, 2026.
Share This Post
